Digoxin Revisited: An Updated Review in the Light of Recent Trials
DOI:
https://doi.org/10.14740/cr2287Keywords:
Digoxin, Rheumatic heart disease, Heart failure, Public healthAbstract
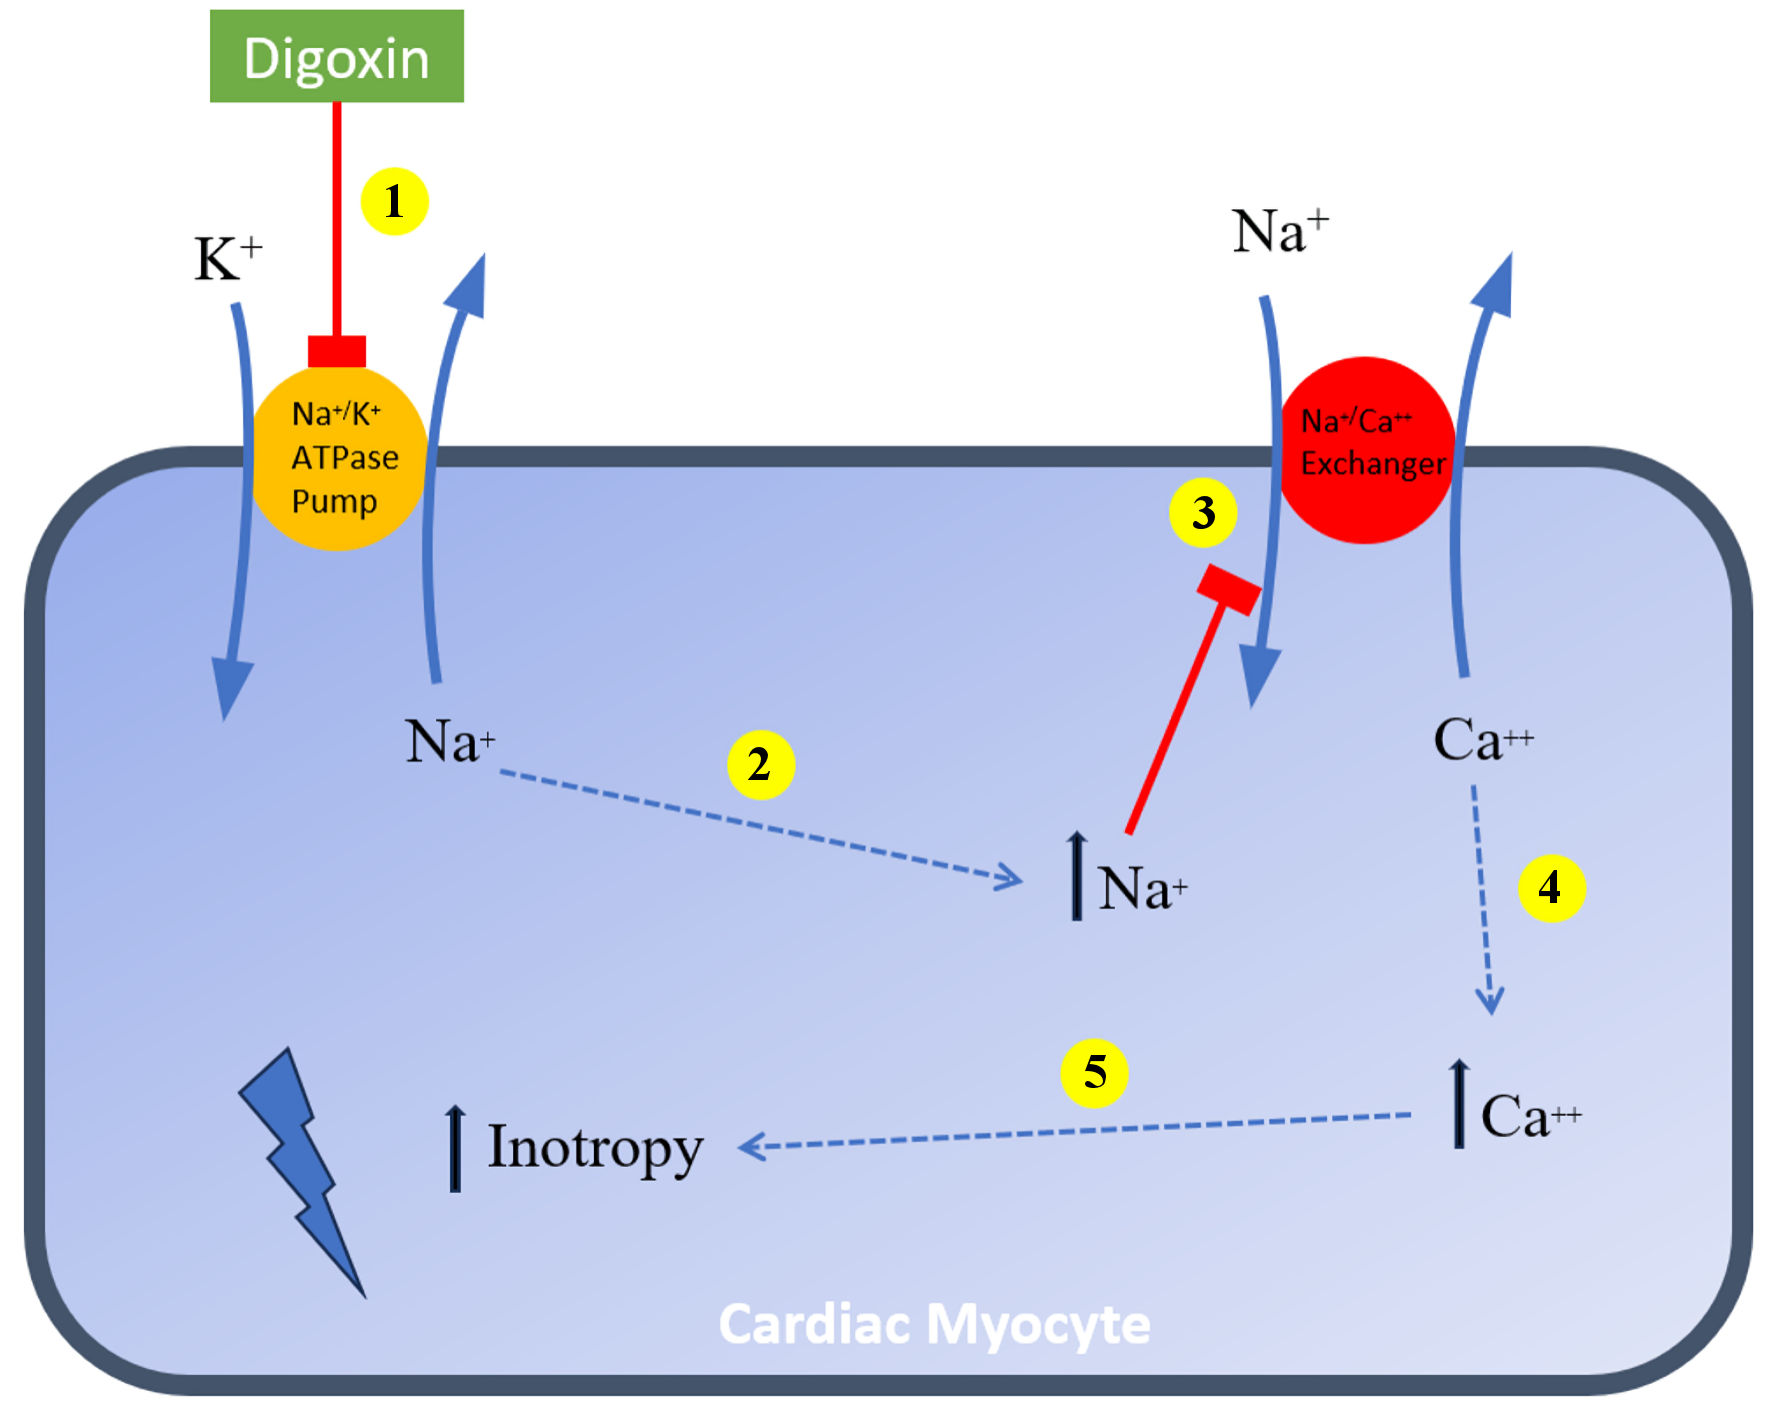
Isolated from Digitalis species following William Withering’s 1785 work on foxglove, digoxin inhibits myocardial Na+/K+-ATPase, raising intracellular calcium and vagal tone to produce inotropic, rate-controlling, and neurohormonal-deactivating effects. The foundational DIG trial (1997) showed no mortality benefit but reduced heart failure hospitalizations, prompting a progressive guideline downgrade. Three decades later, DIGIT-HF (2025, digitoxin) and DECISION (2026, low dose digoxin) retested cardiac glycosides atop modern four pillar guideline-directed medical therapy (GDMT). DIGIT-HF significantly reduced the composite of death or worsening heart failure (hazard ratio (HR), 0.82), while DECISION showed a numerical but nonsignificant benefit. A pooled meta-analysis of DIG, DIGIT-HF, and DECISION (9,013 patients) confirmed a consistent 15% reduction in worsening heart failure events across three decades of changing background therapy, without a significant mortality effect. The Dig-RHD trial addressed an unstudied population: symptomatic rheumatic heart disease (RHD), a chronic valvular heart disease that results from permanent damage to cardiac valves due to group A streptococcal infection. RHD affects roughly 40 million people and causes approximately 300,000 deaths annually, disproportionately in low- and middle-income countries. In 1,769 patients randomized across 12 Indian centers, digoxin significantly reduced the composite of death or new-onset/worsening heart failure (31.4% vs. 35.5%; HR, 0.82; 95% confidence interval (CI), 0.70 to 0.97; P = 0.02), with greater benefit in atrial fibrillation, women, and patients with low body mass index (BMI), and a number needed to treat of approximately 14 over 2 years. Digoxin is not a mortality-reducing drug, but pooled contemporary evidence establishes it as a reproducible, low-cost tool for reducing heart failure events, now supported for the first time by high-quality randomized data in RHD, a population with substantial global burden and no prior evidence-based medical therapy. These findings warrant reconsideration of digoxin’s guideline status and development of RHD-specific recommendations.
Published
Issue
Section
License
Copyright (c) 2026 The authors

This work is licensed under a Creative Commons Attribution 4.0 International License.